In my two decades of clinical practice—whether I am consulting with families in the Philippines or working with the vibrant international community in Alicante, Spain—I have often described Parkinson’s disease as a “biological drought.” For years, we focused on the lack of dopamine “rain” in a specific part of the brain called the basal ganglia. We treated the disease like a broken door hinge: if we could just grease the hinge with Levodopa or zap it with an electrical probe (Deep Brain Stimulation), we could keep the door swinging.
But as of February 2026, the paradigm has shifted. A monumental study from Washington University in St. Louis, published in Nature, has revealed that Parkinson’s isn’t just a “hinge” problem—it is a “wiring” problem. By identifying the Somato-Cognitive Action Network (SCAN) as the neurological heart of the disease, we finally have the “GPS coordinates” for the source of the glitch.
This discovery moves us away from generalized medicine and into the era of Precision Neuromodulation. We are no longer just managing symptoms; we are re-tuning the network that links our thoughts to our actions. As your health thought partner, let’s explore why this 2026 breakthrough is the most significant leap in Parkinson’s research in decades.
1. The SCAN Discovery: The Bridge Between Thought and Action
To understand why this matters, we first have to understand what the SCAN actually is. First described in 2023 by Dr. Nico Dosenbach, the SCAN is a specialized network within the motor cortex.
The Translator of the Brain
In a healthy brain, the SCAN acts as the ultimate “translator.” Its job is to take a high-level thought—“I want to stand up and walk to the kitchen”—and translate it into the specific, millisecond-timed muscle contractions required to execute that movement. It doesn’t just send the signal; it monitors the movement as it happens, adjusting for balance and obstacles in real-time.
Why Parkinson’s is a “SCAN Disorder”
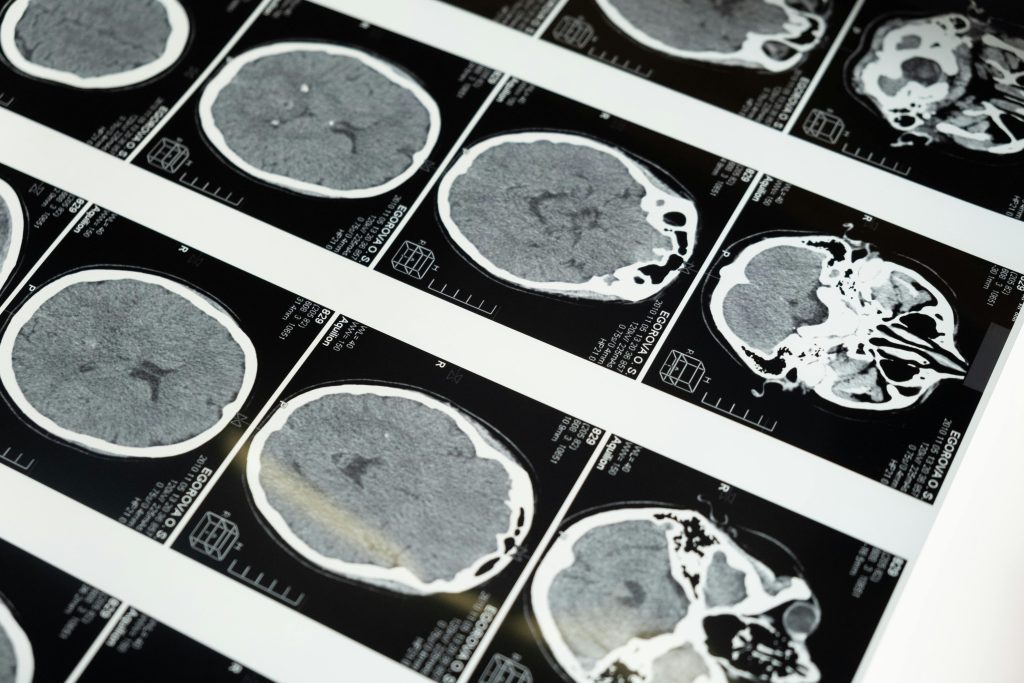
The 2026 research, led by an international team including Changping Laboratory and WashU Medicine, analyzed brain imaging from over 800 participants. They found that in Parkinson’s patients, the SCAN isn’t just “weak”—it is hyperconnected.
- The Glitch: The SCAN is overly connected to the subcortex (the region responsible for motor control and emotion).
- The Static: This hyperconnectivity creates a kind of neurological “static” or “crosstalk.” It’s like trying to listen to a radio station where two signals are playing at the same time. You can hear the music, but there’s so much noise you can’t dance to the beat.
2. The Hyperconnectivity Glitch: When the Brain’s “Radio” Gets Static
For decades, we associated Parkinson’s primarily with the basal ganglia. We thought the tremors were just a result of those cells dying off. But the SCAN discovery reveals a much broader network dysfunction.
The Systems-Wide Impact
Because the SCAN is a high-level network, its failure explains why Parkinson’s symptoms are so diverse and often “non-motor.” When this network is hyperconnected, it doesn’t just affect your gait; it disrupts the signals for:
- Digestion: Explaining the chronic constipation and GI issues many patients face.
- Sleep: Explaining the REM sleep behavior disorders and insomnia.
- Motivation and Mood: Explaining the apathy and depression that often precede tremors by years.
- Cognition: Explaining why “thinking while walking” becomes so difficult as the disease advances.
Normalizing the Circuit
The 2026 study found that every successful treatment for Parkinson’s—from DBS to medications—works because it inadvertently reduces this hyperconnectivity. However, these treatments were “blunt instruments.” They hit the whole area, hoping to quiet the static. The goal now is millimeter-level precision: target the SCAN specifically to restore a balanced relationship between thought and action.
3. Precision Neuromodulation: Moving from Surgery to Millimeters
The most startling data from the WashU study comes from the clinical trial of SCAN-targeted Transcranial Magnetic Stimulation (TMS). TMS is a non-invasive procedure that uses magnetic pulses to stimulate specific brain regions through the scalp.
The 2.5x Improvement Gap
In the trial, 18 patients received stimulation specifically aimed at their SCAN network using “millimeter-level accuracy.” Another 18 patients received stimulation to “nearby” motor regions—the traditional way TMS has been performed for years.
The Results Were Undeniable: Precision TMS vs. Conventional Methods
When it comes to treating clinical depression, where we aim matters just as much as how we treat. Recent data highlights a massive gap in effectiveness between traditional methods and new, mapping-based technologies.
| Treatment Approach | Response Rate | Clinical Significance |
| Conventional TMS (General Region) | 22% | Marginal benefit |
| SCAN-Targeted TMS (Precision) | 56% | Significant clinical breakthrough |
Why This Matters for the Patient
A 56% response rate is more than double the effectiveness of previous non-invasive attempts. This level of success rivals the results of Deep Brain Stimulation (DBS) but without the need for invasive brain surgery.
- Early Intervention: Because it’s non-invasive, we can start treating patients with neuromodulation much earlier. Currently, DBS is a “last resort” because of the surgical risks. In 2026, SCAN-targeted TMS could be a “first-line” defense.
- Personalized Care: Every brain is wired slightly differently. By mapping an individual’s SCAN before treatment, doctors can deliver magnetic pulses to the exact “sweet spot” where their hyperconnectivity is most severe.
4. Beyond Tremors: How SCAN Explains Sleep, Digestion, and Mood
As a geriatric specialist, I am particularly interested in how the SCAN network explains the “hidden” side of Parkinson’s. In my Full Circle protocol, we look at Systemic Resilience. We know that the brain doesn’t live in a vacuum.
The CKM Syndrome Link
In 2026, we are increasingly looking at the Cardiovascular-Kidney-Metabolic (CKM) connection. If the SCAN network is hyperconnected and “noisy,” the body’s internal systems suffer.
- Autonomic Failure: The “static” in the SCAN disrupts the signals to the gut and heart.
- The Inflammation Loop: Poor sleep and digestion lead to systemic inflammation, which further damages the brain’s remaining dopamine-producing cells.
Intellectual Honesty: We aren’t just “Greasing Hinges”
We have to be honest with ourselves: treating Parkinson’s with just Levodopa is a 20th-century strategy. In the 21st century, we must treat the network. By quieting the hyperconnectivity in the SCAN, we may be able to improve sleep and digestion before we even address the tremor. This improves the patient’s “Healthspan”—not just their ability to walk, but their ability to live with vitality.
5. The 2026 Roadmap: Wearables and Ultrasound in Parkinson’s Care
What does the future of this discovery look like? Dr. Nico Dosenbach is already launching clinical trials through Turing Medical, a WashU startup, to bring this technology into the home and the clinic in less invasive ways.
Surface Electrode “Bandages”
One of the most exciting projects for 2026 is the use of surface electrode strips. These are essentially high-tech “bandages” that sit over the SCAN regions on the scalp.
- Target: Gait problems and “freezing” during walking.
- Method: Delivering subtle electrical stimulation to quiet the SCAN “static” while the patient moves, helping them maintain a steady stride.
Low-Intensity Focused Ultrasound
Another frontier is Focused Ultrasound. Unlike the high-intensity ultrasound used to “burn” away problematic tissue, low-intensity ultrasound uses acoustic energy to gently “nudge” the SCAN network back into balance. It offers a deeper level of precision than magnetic pulses and can reach regions of the SCAN that are tucked further into the brain’s folds.
The Shift to “Neurological Health”
The realization that Parkinson’s is a SCAN disorder means that our diagnosis will become much more precise. Instead of just “tremor assessment,” 2026 diagnostics will involve Connectivity Mapping. We will see the disease in the wiring long before the patient feels the first tremor.
How I Can Help You Navigate the SCAN Revolution
At Puente Costa Blanca, we are already integrating these “network-thinking” principles into our Integrated Neuro-Physical Training.
Online Medical Consultations (Philippines & Global)
For my global community, I offer secure consultations via SeriousMD.
- SCAN-Based Risk Audit: Reviewing your non-motor symptoms (sleep, mood, digestion) to see if they point to early network dysfunction.
- Neuromodulation Roadmap: Discussing if you are a candidate for precision TMS or ultrasound trials.
BOOK YOUR MEDICAL CONSULTATION NOW ON SERIOUSMD
Geriatric Rehab & Anti-Aging Clinic (Alicante & Costa Blanca, Spain)
For the international community in Spain, we bridge the gap between advanced research and daily functional autonomy.
Visit our local sites: Puente Costa Blanca (.com) |Puente Costa Blanca (.es)
- Neuro-Functional Training: Specific brain-body drills (like the Johns Hopkins SOP drills) designed to challenge and “re-tune” the thought-to-action bridge.
- Sarcopenia & Vitality: Building the physical strength that supports the cardiovascular health necessary for effective neuromodulation.
- Autonomy & Comfort: Proving that your “biological switches” are something you can influence through your daily choices.
Final Thoughts from Dr. Marie
The discovery that Parkinson’s is a SCAN disorder is a gift of clarity. It tells us that the brain’s struggle to move is a struggle to communicate. By focusing on the network, we aren’t just fighting a disease; we are restoring the “Bridge of Action” that allows you to be the pilot of your own life.
Let’s look at your “wiring” and protect your future together.
Dr. Marie Gabrielle A. Laguna, MSc, M.D., FPCP, FDip (Geriatric Rehab, UK) Internal Medicine & Senior Health Specialist